
Blog
Dental hygiene tips for healthy teeth & gums
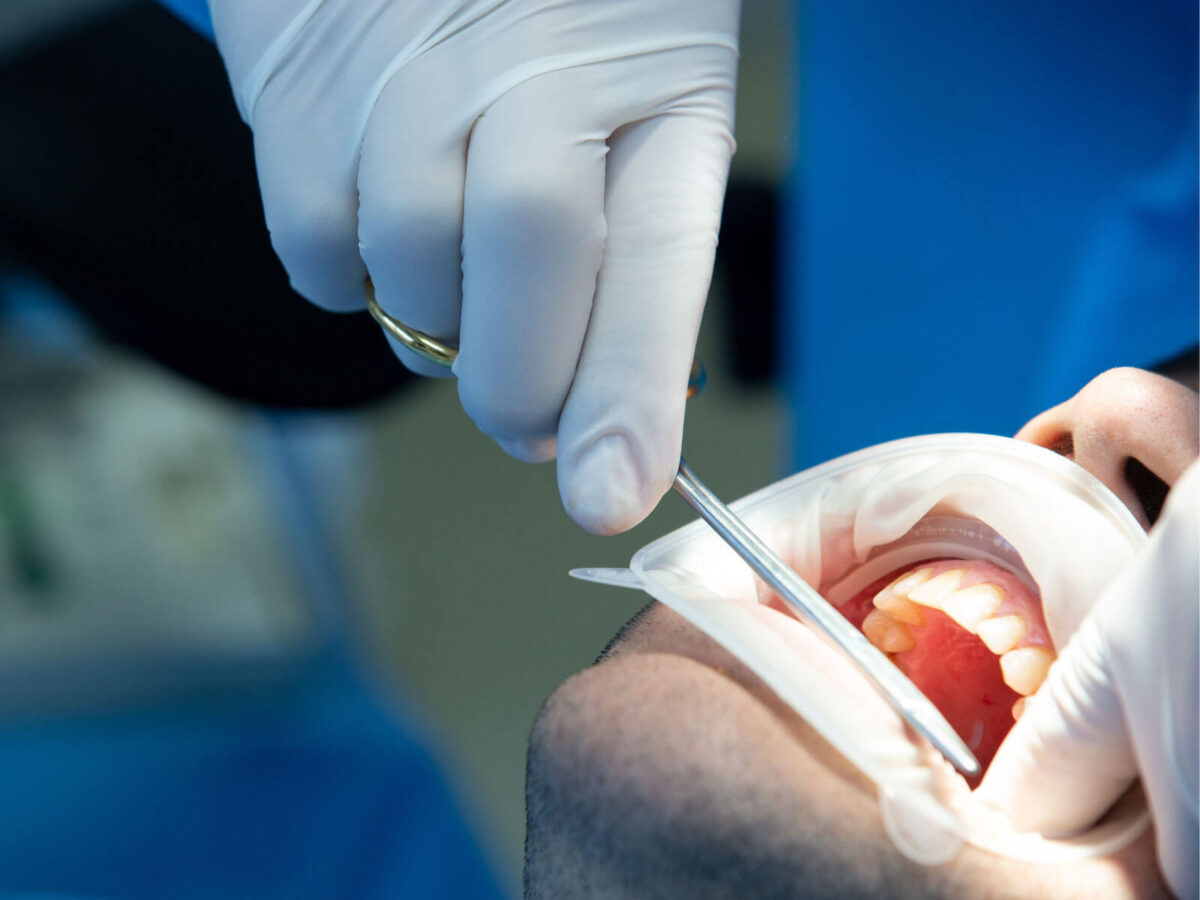
When Is a Root Canal (RCT) Required? Signs You Need One
The pain that sends people to a dentist at eleven at night is usually the same one. It builds slowly through the evening. It doesn’t settle when you lie down, and painkillers take the edge off for about ninety minutes at a time.
When is RCT required, or root canal treatment as it’s better known, comes down to one question underneath all of that. Is the pulp inside the tooth inflamed beyond recovery, or infected outright?
Everything else – symptoms and tests and X-rays – exists to find that out. Treatment itself is a matter of clearing the tissue out, cleaning the canal system, and sealing it. The tooth stays where it is and carries on working.
Plenty of teeth that need treating don’t hurt at all. Some that hurt badly turn out to need a filling. Which is why the answer comes from a dentist rather than from a list of symptoms on a screen.
TL;DR
When is RCT required? When the pulp inside a tooth is irreversibly inflamed or infected, however it got that way.
Pain that lingers after cold is the most telling symptom. So is pain that wakes you, or throbs harder when you lie flat.
Dead pulp often produces no pain at all. A darkening tooth or a small bump on the gum can be the only sign anything is wrong.
Treated teeth last. One long-term study put survival at 97% after ten years, and 68% still in place at thirty-seven.
Extraction makes sense when there isn’t enough sound tooth left to rebuild, or when the root itself has cracked.
When Is RCT Required
Deep decay is the most common route in. Bacteria work through enamel, then dentine, then reach the pulp chamber.
Trauma is the second. A knock to a front tooth can sever the blood supply at the root tip without cracking anything you’d see, and that tooth dies quietly over the months or years afterward. People often can’t connect it to the incident when it eventually shows up.
Cracks running into the pulp open a direct path for bacteria. That’s why sharp pain on biting gets investigated properly instead of monitored.
Repeated dental work is the one nobody expects. Every filling, every replacement, every preparation adds insult to the pulp underneath, and a tooth that’s been restored several times can eventually give up with no new decay involved.
A failed prior root canal is its own category. Bacteria survive in canals that weren’t fully cleaned or sealed the first time, and what gets discussed at that point is retreatment.
What Are the Most Common Root Canal Symptoms
Pain that outlasts the trigger. Cold or hot food causes a jolt, and instead of fading within a second or two, it hangs on for thirty seconds, sometimes minutes. Of everything on this list, this is the one dentists take most seriously.
Pain at night, or when you lie down. Blood pressure to the head rises when you’re horizontal, and that adds pressure inside a chamber that’s already inflamed.
Throbbing that arrives on its own. No hot drink, no cold, no biting. Pain with no trigger at all suggests the inflammation has gone past the point of coming back.
Tenderness when you bite. By this stage, the infection is past the root tip, in the ligament that holds the tooth in its socket. You’ll be able to point straight at the one that hurts.
A small bump on the gum. Sometimes recurring, occasionally leaking something that tastes foul. That’s a sinus tract draining an abscess, and it’s about as definitive as symptoms get.
Swelling of the face or jaw needs same-day care. Not an appointment next week. Lower molars are the ones to watch, because swelling in that space can reach the airway, and facial swelling with fever or difficulty swallowing is an emergency room rather than a dental appointment.
Tooth Pain That Won’t Settle?
Get it diagnosed properly before the infection spreads further.
Which Teeth Need a Root Canal Without Hurting
Some teeth give you nothing to work with. Pulp dying gradually means the nerve stops signaling, so the tooth feels completely fine while an abscess develops quietly at the root tip. It turns up as a dark shadow on an X-ray taken for something else.
Discoloration is the other silent one. A tooth going gray or brown next to its neighbors usually means the pulp died a while back, and front teeth do this years after a childhood knock nobody remembers.
The one to watch for is a tooth that hurt badly and then stopped. That reads like recovery, and it almost never is. What happens is the nerve finishes dying off, and the infection carries on with nothing left to signal pain.
How Does a Dentist Confirm RCT Is Required
Pulp testing comes first, usually a cold stimulus applied to the tooth and to its neighbors for comparison. No response at all points toward dead pulp. A response that keeps hurting after the cold is removed points toward inflammation that won’t reverse.
Then they tap it. Percussion testing tells them whether the tissue beyond the root tip has gotten involved, which is a different question from whether the pulp itself is dying.
Radiographs show what the outside of a tooth can’t. A darkened area at the root tip means bone loss from infection. Worth knowing that it takes weeks or months to appear, so a clean X-ray on its own rules nothing out.
Complicated cases get a cone beam CT scan for a three-dimensional view. That’s how extra canals get found, and root fractures and lesions plain films miss entirely.
Root Canal vs Extraction – How the Choice Gets Made
Saving the tooth is the default, and the long-term data backs that instinct. One study followed root-treated teeth for up to 37 years. At ten years, 97% were still in place. At thirty-seven, 68% were.
Population-level numbers land lower and still look good. An 11-year cohort drawn from Korean national insurance records, covering over 1.4 million teeth, put cumulative survival at 88.37%.
Extraction wins in specific circumstances. Not enough sound structure above the gum to hold a restoration. A vertical fracture running down the root. Severe gum disease around the same tooth, which that 37-year study named as one of the strongest predictors of a tooth eventually coming out anyway.
Cost belongs in the discussion. Compare root canal vs extraction on the day and extraction wins easily, which is the comparison most people make. What it leaves out is the implant or bridge that follows, which lands well above what the root canal and crown would have cost.
FAQ
Does a root canal hurt?
It’s done under local anesthetic and feels much like having a filling. The days before the appointment are the painful part.
Can antibiotics fix it instead?
No. They’ll bring swelling down for a while, but nothing reaches bacteria sitting inside a canal that no longer has a blood supply.
Do I need a crown afterward?
On back teeth, usually. An uncovered molar splits eventually, and delaying the crown is the main reason treated teeth get lost.
How many appointments is a root canal?
One or two visits for most teeth. Molars with several canals take longer, and so does anything that needs medication left inside between appointments.
Conclusion
The symptoms worth acting on are specific ones. Pain that lingers after cold. Pain arriving at night with nothing to provoke it. Tenderness when you bite. A bump on the gum near a tooth.
Absence of pain proves very little, which is the part that catches people. Plenty of teeth needing treatment turn up on a routine X-ray taken for something else entirely, in mouths that felt fine.
When RCT is required is a question a dentist answers with a cold test and a film, not one you can settle at home. Mention the history at the appointment. A tooth that hurt badly in April and went quiet in May is telling you something, and it isn’t that the problem resolved.
Find Out What’s Causing the Pain
Get a proper diagnosis and know whether the tooth can be saved.

